Wilson and Company
Wilson and Company
How Long Does It Take to Build a Medical Office?

How Long Does It Take To Build a Medical Office?

The construction is the short part. The calendar is decided by the stages around it, and by a few lead times inside it.


The Stage-By-Stage Answer

The medical office construction timeline has six clocks that run mostly one after another. For a typical interior build-out of a medical office suite, here is the sequence with the ranges we quote, matching the stages already published on this page:
  • Design and drawings: roughly 6 to 12 weeks of design decisions, with construction drawings running 2 to 3 months for a full medical fit-out.
  • Estimating and pricing: 2 to 3 weeks once drawings are complete enough to price.
  • Contracts: about a month for review, negotiation, and signatures. Owners rarely budget calendar time for this stage, and it is real.
  • Permitting and plan review: 2 to 4 months through a municipal process, depending on the jurisdiction and the review cycle count.
  • Construction: 12 to 16 weeks for a suite in the 10,000 square foot range.
  • Inspections and closeout: final inspections, corrections, and the certificate of occupancy.
Empty Corridor And Nurse Station Desk In Modern Medical Office

The Perfect Scenario Versus the Realistic One

Add up the best case of every stage and you get a number nobody should put in a lease. The perfect scenario assumes design decisions on the first pass, pricing with no scope questions, a contract nobody’s attorney marks up, a permit approved on the first review cycle, and a build with no surprises. Any one of those happens regularly. All of them together almost never do. The realistic plan assumes at least one stage runs long, and builds the lease commencement, financing draw schedule, and staff hiring dates around the realistic total rather than the perfect one. The stages that most often run long are the two an owner controls least directly: permitting, because the review cycle count belongs to the jurisdiction, and design, because every revisited decision restarts a piece of the drawing work. Facility-specific healthcare construction regulations also affect what the design team must address before the plans go in for review. As a reference point from our own work: a 3,500 square foot clinic in Palm Bay, Florida went from design through doors open in roughly seven months delivered design-build, a project where the stages were compressed by running design and pricing together instead of one after the other. That is what a good outcome looks like at that size, and it still took most of a year once the early decisions are counted. architect looking at blueprint

Why Timelines Slip: The Lead-Time Arithmetic

Here is the arithmetic that catches practice owners off guard. A build-out may run three to four months, but specialty items inside it can carry lead times of roughly three months on their own. Doors with hardware are the classic example: order them at the start of construction and they arrive when the job should be finishing. The schedule killer is not slow work, it is a purchase order written too late. That is why submittal approval, the cycle where the contractor proposes specific products and the design team approves them, is usually the real critical path. Every week a submittal sits unreviewed pushes a delivery date that pushes an installation date. The same chain logic applies to inspections: one failed inspection does not cost one day, it costs the reinspection queue time plus every trade that was sequenced behind the corrected work. The last slip source is capability mismatch. A contractor or subcontractor taking on a facility type they have not built learns on your schedule. Mechanical trades are where this shows up most in medical work, because clinical ventilation requirements are unforgiving. Two workers wearing hardhats standing in big empty hall of new building looking at construction plan, extreme long shot

What Actually Keeps a Schedule

The owners who hit their dates do four things. They make design selections early and completely, because a late finish selection reprices and resequences work. They ask their contractor for the long-lead item list on day one and release those orders first. They treat submittal turnaround as a scheduled commitment for the design team, not a courtesy. And where the project allows it, they talk to their contractor about phasing the permits so early work starts while later phases are still in review. If you are working against a lease commencement date or a financing deadline, bring the whole sequence to a contractor who specializes in healthcare construction in Orlando and ask them to map the six clocks against your date. A contractor who knows the local review process can tell you which stages have slack and which do not, before you have committed to a date the sequence cannot deliver. That conversation costs nothing and it is the single cheapest schedule protection available.  

Frequently Asked Questions

How long does a medical office build-out take?

Construction itself typically runs 12 to 16 weeks for a suite around 10,000 square feet. The full journey, design through certificate of occupancy, is usually far longer once drawings, pricing, contracts, permitting, and inspections are counted. Plan around the whole sequence, not the construction stage alone.

What causes the biggest delays in medical office construction?

Long-lead materials ordered late, slow submittal approvals, and failed inspections. Specialty items such as doors with hardware can carry lead times close to the length of the build itself, so the schedule is usually lost in purchasing and approvals rather than in fieldwork.

Can permitting run at the same time as other stages?

Sometimes. Some projects can phase permits so early-stage work is permitted and started while later phases remain in review, and private provider plan review can shorten the review cycle where jurisdictions allow it. Ask your contractor what your jurisdiction supports before assuming a serial timeline. Continue Reading
How to Renovate a Medical Office Without Closing

How to Renovate a Medical Office Without Closing the Practice

The renovations that keep a clinic open are not gentler versions of normal projects. They are differently designed projects, and the design happens before anyone lifts a tool.


The Standard is Monday Morning

If you’re closing a practice for a medical office renovation, you need to budget more than the construction costs. Every dark week is lost visits, rescheduled patients who may not come back, and staff sitting idle on payroll. For those reasons, most medical office renovations happen around a clinic that stays open, and that changes what success even means. Early medical office construction planning should identify which exam rooms, entrances, and patient routes must remain available while the work is underway. Here is the measure we have learned to build to: the work is judged by what the practice finds on Monday morning, not by what the crew accomplished on Friday. A renovation can be perfectly built and still fail the practice if patients walk past dust, cluttered corridors, or a waiting room that smells like a job site. Cleanliness, not craftsmanship, is what an operating clinic’s patients and staff actually experience during construction, and it is the thing they will remember. That standard has operational consequences. On our occupied clinic work, cleaning crews are dispatched at the end of each work window, Sunday afternoons included, so the practice opens to a space that looks like a clinic rather than a project. The craftsmanship still has to be there. The point is that in an occupied building it is the entry ticket, not the finish line.  

Containment is a Design Decision, Not a Tarp

Patients in the building while walls come down means the first real design question is separation: how the work zone is sealed off from the care zone. That answer should be tiered to the work being done. Short-duration, low-dust tasks call for a different level of barrier than a multi-week demolition, and treating every task like the worst case wastes money while treating the worst case casually risks far more than comfort. In practice, the tiers run from a simple sealed enclosure around a small, quick task, up through full floor-to-deck temporary partitions with sealed joints, protected walk paths, and controlled access for anything long-running or dust-heavy. What sets the tier is not how the work looks but what it releases and how long it runs: cutting into a ceiling for a day and demolishing a suite for three weeks are different exposures, and the plan should price and build them differently. For heavier work, medical settings raise the bar beyond a sealed partition. The work zone is held under negative air pressure, so air flows from the clinic into the construction area and out through filtration, never the reverse. Keeping that pressure differential is an active job: every breach in the barrier, every propped door, every filter change is a chance to lose it. On projects with infection-sensitive populations, an infection control risk assessment before work starts is what decides the containment level, and the barrier plan follows from it. We have held negative pressure through a renovation inside an operating pharmaceutical distribution facility, and the discipline is the same in a clinic corridor: the barrier is a system you maintain, not a wall you build once. One life-safety trigger deserves its own paragraph, because it surprises practice owners and undisciplined contractors alike. If the renovation requires draining the building’s sprinkler system, the building does not simply carry on. A drained system typically puts the building on a fire watch, a continuous human patrol required until the system is restored. That is cost, staffing, and coordination that belongs in the plan from day one, not discovered the week the plumber needs the system down.
The barrier is a system you maintain, not a wall you build once.
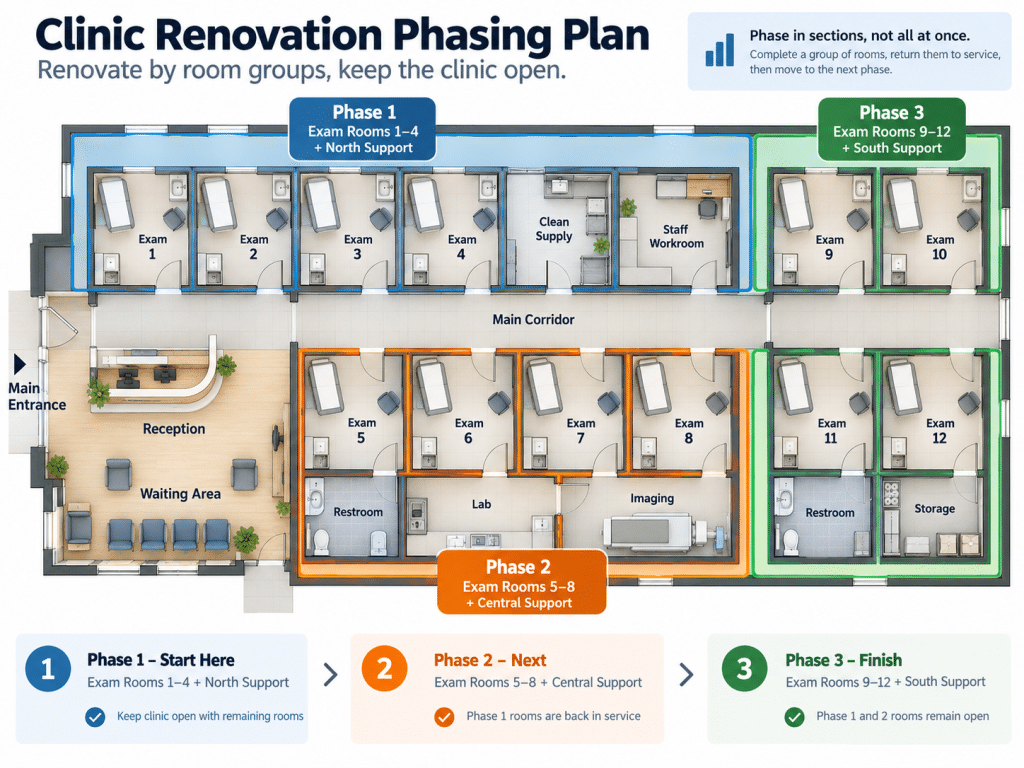
To renovate a medical office without closing, your contractor should have a plan for phased work

Phasing: Split the Space, Then Split the Calendar

An occupied renovation is really a sequence of small renovations. The floor gets divided into phasing units, each one taken out of service, renovated, cleaned, and handed back before the next begins. The practice keeps operating in the balance of the space the whole time. The handback is a ritual worth formalizing. A phase is not done when the trades finish; it is done when it has been cleaned to clinical standards, walked by the administrator, and returned with everything working, because the practice will restock and reschedule against that space the same day. A contractor who treats the handback as a punch-list formality will hand the clinic a room it cannot use, and the schedule credit for finishing evaporates. Two scheduling levers matter most. The first is the work window: some tasks belong in normal hours behind containment, some after hours, and the loudest or riskiest in weekend windows when the clinic is empty. The second is permitting structure: on some projects, phasing the permits themselves lets early phases start while later phases are still in review, instead of holding the whole renovation for one master approval. Both levers get pulled in preconstruction, which is why an occupied renovation that starts without a phasing plan is already late. Communicate the phases spatially, not just by calendar. Telling a clinic administrator the project runs March through June tells them nothing they can staff around. Telling them exam rooms one through four are out of service for these three weeks, then five through eight for the next three, lets them load schedules, move providers, and warn patients. The clinic thinks in rooms, so the schedule should speak in rooms. The same room-based scheduling applies to dental office construction, where treatment equipment, imaging, and utility connections can affect which rooms are available during a renovation. The proof this works at scale: our team has run seven to eight occupied clinic refreshes simultaneously across a Central Florida health campus at Hunter’s Creek on a two-month deadline, with the practices seeing patients throughout. That is not a special project type. It is the same phasing discipline applied at volume.  

The Communication Protocol Does Half the Work

Ask administrators of clinics that have been through a renovation what went wrong, and the answer is rarely the construction. It is the surprise: the corridor that closed without warning, the noise during a procedure, the patient who walked into the wrong entrance. Occupied work runs on a communication protocol as deliberate as the containment plan. The version we run puts the clinic administrator, the owner’s representative, and the key subcontractors on the same call, so decisions get made once, with everyone who has to live with them present. Between calls, a daily touchpoint at the end of each work day covers what happened, what is next, and what the practice will notice tomorrow. And before any of it, expectation-setting: walking the administrator through what each phase will sound like, smell like, and block off, before it happens, so the front desk is answering patient questions with information instead of apologies. The expectation-setting deserves to be scripted, not improvised. The administrator should leave that conversation able to answer the three questions patients actually ask: where do I park and enter this month, will my appointment be affected, and when is it over. Arm the front desk with those answers per phase and the renovation largely disappears from the patient experience, which is the entire point.

“We can’t always guarantee that operations are not impacted, but we can complete projects with minimal impact utilizing phasing and temporary partitions.”

Wilson & Company, Renovations & Active Clinics: How to Minimize Downtime
 

What Staying Open Honestly Costs

None of this is free, and pretending otherwise is how occupied renovations go wrong. Phasing stretches the calendar, because the same scope built in sequence takes longer than built all at once. Containment, protection, after-hours premiums, and end-of-window cleaning are real line items. A renovation plan that shows the same price and duration occupied as it would vacant has not actually planned for occupancy. The comparison that matters is the whole ledger. Weigh the construction premium against the revenue a closure forfeits: weeks of lost visits, rescheduled patients who drift to other providers, and idle staff. For most practices that math lands firmly on staying open, but it should be run with real numbers for your practice, not assumed.  

Plan For the Inspection Chain, Not Just the Inspection

In an occupied renovation, schedule risk compounds in a specific way. A failed inspection does not cost a day; it costs the reinspection queue, plus every trade sequenced behind the corrected work, plus, uniquely to occupied projects, the phase handback date the practice has already staffed around. A slip that a vacant building absorbs quietly lands on a clinic as broken promises to patients. A review of applicable healthcare construction regulations during preconstruction helps the team account for life-safety and accessibility requirements before inspection dates are fixed. The defenses are unglamorous: pre-inspection walkthroughs by the contractor before the official one, trades scheduled with buffer around inspection dates, and phase durations set with the honesty to include correction time. When a phase does slip, the spatial communication habit pays for itself, because the administrator hears which rooms are affected and for how long, immediately, rather than discovering it.  

What To Settle Before You Sign Anything

If you are weighing a renovation of your operating practice, settle five things with your contractor before committing: the containment approach for each type of work and who maintains it, the phasing map in rooms rather than dates, the work-window rules your patients and neighbors can live with, the communication cadence and who is on the call, and the life-safety plan including what happens if systems must come down. A contractor experienced in occupied medical work will have specific answers, and several of these questions are answered differently for a clinic than for any other occupied building. The renovations that keep practices open are decided in preconstruction. By the time containment goes up, the outcome is mostly already chosen. If a renovation of your operating practice is on the horizon, start those five conversations early, while every answer is still cheap to change.  

Frequently Asked Questions

Can a medical office stay open during a renovation?

Yes, and most do. The renovation is phased so a portion of the space is under construction while the rest operates, separated by sealed containment, with heavier work pushed to after-hours and weekend windows. The tradeoffs are a longer overall schedule and added cost for phasing and protection.

How is dust and infection risk controlled during clinic renovation?

Through tiered containment matched to the work: sealed barriers for lighter tasks, and negative air pressure with filtration for heavier work, so air never flows from the work zone into patient areas. On infection-sensitive projects, an infection control risk assessment sets the required level before work begins.

How disruptive is the noise for patients?

It depends on scheduling more than on the work itself. Loud demolition and drilling belong in after-hours or weekend windows, and the phasing plan should tell the practice exactly which days carry noise risk so procedures can be scheduled away from them. Surprise, not sound, causes most complaints.

Does an occupied renovation cost more than closing the practice?

The construction usually costs more, because phasing, containment, off-hours work, and cleaning are real line items. The comparison that matters is total cost: weeks of lost patient revenue and rescheduled care during a closure typically outweigh the construction premium, which is why most practices choose to stay open. Continue Reading

What Practice Owners Should Look for in a Medical Office Construction Estimate

Most practice owners will evaluate exactly one set of construction bids in their career. The contractors pricing the work do this every week. Here is how to close that gap in an afternoon.


The lowest number is a claim, not a price.

When three bids land on a practice owner’s desk, the temptation is to treat them as three prices for the same thing. They almost never are. Each number is a claim about scope: what that contractor believes the drawings require, what they included, what they quietly left out, and how much risk they priced. The real comparison is between scopes, and the estimate document is where a scope shows itself or hides. This matters more in medical work than in ordinary commercial space, because clinical requirements, ventilation, plumbing density, power for equipment, code obligations, etc. are exactly the items a thin bid skips. The gap between a complete medical estimate and an optimistic one does not disappear when you sign. It comes back as change orders, on your schedule and your budget, after your leverage is gone.  

Red flags you can spot in five minutes

A few patterns reliably signal a number you cannot trust, and none of them require construction expertise to see.
  • A price that drops 10% or more with no change in scope. If the number can fall that far because you hesitated, the first number was padding or the second one is missing something. Either way you have learned how the contractor negotiates.
  • Single-line subcontractor amounts. “Electrical: $180,000” tells you nothing about what the electrician included. A real estimate carries enough breakdown to show what is behind the trades that dominate medical work.
  • No stated exclusions. Every estimate excludes something. One that does not say what it excludes has not told you where the gaps are, and the gaps are where the change orders live.
  • Vagueness about what happens to cuts. When a low bidder trims to win, the cuts land somewhere, and they usually land on what you can see: the finishes, fixtures, and details your patients will look at every day.
Watch both outliers, not just the high one. Owners instinctively interrogate the expensive bid and celebrate the cheap one. Do the opposite as well: ask the low bidder what everyone else saw in the drawings that they did not, and ask the high bidder what they saw that everyone else missed. A meaningful spread between bids means the bidders priced different projects, and you need to know which project is actually in the drawings. Sometimes the high bidder is the only one who noticed the structural work your imaging room requires; sometimes the low bidder has simply not priced it. Both answers are worth the ten minutes it takes to get them.  

What a complete estimate itemizes

The rule that governs everything in an estimate is simple: not drawn means not priced. A contractor prices the documents in front of them, not the project in your head. If the drawings do not show it, it is not in the number, and the honest estimates say so in writing. That is why the inclusions and exclusions list is the most important page of the document, more important than the total. The second thing to demand is a general conditions breakdown. General conditions are the costs of running the project itself: supervision, project management, temporary facilities, cleanup, safety, and the like. Thin bids bury them in a single line or scatter them invisibly through trade prices. Our own bid summaries itemize general conditions line by line across pre-construction, construction, and post-construction, because an owner who can see what running the job costs can compare bids on substance instead of totals. Ask every bidder for the same breakdown, and note who resists. Third, look for how the estimate handles what is not yet decided. Medical projects always carry decisions that come later: equipment selections, finish grades, owner-supplied items. A complete estimate names those open decisions and carries stated allowances for them, so you know which parts of the number are firm and which are placeholders that will move. Understand how an allowance behaves, because it is the part of the number most likely to change. An allowance is a budget guess for something not yet selected: if the estimate carries an allowance for flooring and you later choose a product that costs more, the difference is added to the contract, legitimately. That is not a contractor failing; it is how allowances work. What separates a fair estimate from a manipulative one is the realism of the guesses. A bidder can make a total look small by setting every allowance at the cheapest conceivable option, knowing your actual selections will cost more. Compare allowance values across your bids line by line, and ask any bidder whose allowances run noticeably low what those figures would actually buy.
The inclusions and exclusions list is the most important page of the document, more important than the total.
 

The owner-supplied equipment trap

Medical projects carry a scope seam that ordinary commercial work does not: the equipment the practice buys directly. Exam tables, sterilizers, imaging equipment, specialty casework, the owner often purchases these outside the construction contract, and that is where a predictable trap sits. The estimate covers the building; it may or may not cover receiving that equipment, setting it, connecting it, and standing behind the connection when something fails. Force the seam into the open before signing. For every owner-supplied item, the estimate should answer four questions in writing:
  1. Who receives and stores it
  2. Who installs it
  3. Who provides the utility connections it needs
  4. Whose warranty covers what when it does not work
A related check applies to warranty scope generally: ask what the contractor warrants, for how long, and what falls to manufacturers or to you. None of these answers is expensive to get in writing before the contract, but all of them are expensive to discover afterward, usually the week the equipment arrives. The equipment seam is also a drawings problem. An exam room sink is a construction decision, not a finish decision, because it drags plumbing, and plumbing dragged late reprices work that is already built. The more completely equipment is decided before pricing, the smaller this whole category of surprise becomes, which is a reason to resolve equipment selections before bids, not after.  

The contingency line is a maturity test

Practice owners sometimes read a contingency line as an admission of sloppiness, as if a confident contractor would not need one. Lenders read it the opposite way, and the lenders are right. Commercial lenders underwriting medical office construction commonly expect a contingency on the order of 8-10% as a condition of the loan, because they have watched what happens to projects without one. An estimate with no contingency is not braver; it has just moved the same risk into your change orders. Lenders also quietly pad the construction schedule a contractor states before they set the loan terms, which tells you something useful: the people whose money is at stake assume estimates run long and cost more than stated. Build your own plan on the same assumption, and favor the bidder whose estimate already reflects it.  

Questions that expose a thin number

You do not need to know construction to pressure-test an estimate. You need the questions that force scope into the open, asked of every bidder identically:
  • What did you exclude, in writing, and why?
  • What allowances are in this number, and what happens when an allowance is exceeded?
  • Show me your general conditions as line items. What am I paying for you to run this job?
  • What in the drawings is unclear or missing, and how did you price that uncertainty?
  • If I asked you to cut this number by 10%, where exactly would it come from?
 

What this means for your next set of bids

Treat the estimate review as its own small project with its own afternoon on the calendar. Build a simple side-by-side: one row per scope area, one column per bidder, with the exclusions and allowance values called out where they differ. The exercise takes an hour with the documents in front of you, and it converts three incomparable totals into a picture of who priced what. Where a cell is blank for one bidder and filled for the others, you have found either a gap or a hidden assumption, and either one is a question worth asking before signing rather than after. Then put every answer in writing. Scope clarifications that live in phone calls have a way of not existing when the change order arrives. The bidder who welcomes that scrutiny is telling you how they will run your job; so is the one who does not. The estimate is the first deliverable a contractor ever hands you, and it is a sample of everything that follows: their thoroughness, their honesty about risk, and their willingness to show their work. A contractor who itemizes what running your job costs, states exclusions without being asked, and prices uncertainty out loud is showing you the project meetings you will sit in for the next year. Choose the number you understand over the number you like, and most of the expensive surprises in medical construction never reach you.  

FAQs

Why is the lowest construction bid often not the cheapest?

Because bids differ in scope, not just price. A low number that excludes real scope comes back as change orders after signing, when competitive pressure is gone. The comparison that protects you is scope against scope, using each bid’s inclusions, exclusions, and allowances, not total against total.

What are general conditions in a construction estimate?

The costs of running the project itself: supervision, project management, temporary facilities, safety, and cleanup, as distinct from the trade work. A trustworthy estimate itemizes them so you can see what managing your job costs. A single buried line makes bids impossible to compare fairly.

How much contingency should a medical office project carry?

Commercial lenders financing medical construction commonly expect a contingency on the order of 8-10% and treat its absence as a red flag. Whatever the final figure, an estimate that carries no contingency has not eliminated the risk; it has moved it into your future change orders.

What does “not drawn means not priced” mean?

Contractors price the drawings they are given, not intentions. Anything absent from the documents, a wall relocation, an equipment circuit, a plumbing rough-in, is absent from the number. The defense is complete drawings and a written inclusions and exclusions list from every bidder before you compare. Continue Reading
Medical office built by Wilson & Company

Things to Consider Before a Healthcare Construction Project

Healthcare construction requires a different level of planning than a typical commercial build. The space has to support patients, staff, equipment, and day-to-day operations. Depending on the project, construction may also have to take place while some or all of those operations continue. That puts more weight on decisions made before construction begins. Budget matters, but so do workflow, privacy, medical infrastructure, timeline, and the condition of the existing space. Permitting, inspections, code requirements, and unexpected conditions can affect the project as well. Whether you are renovating an existing practice, expanding your facility, or building from the ground up, the following items can serve as a preconstruction checklist for the decisions healthcare owners should work through early. Continue Reading
Oviedo Endodontics-Oviedo FL

How to Expand a Medical Office Without Disrupting Patient Care

Growing into the suite next door sounds simple. What makes it work is occupancy sequencing, decided long before demolition.


The Expansion Problem Nobody Warns You About

A growing practice that expands into adjacent space is running two projects at once: a medical office construction project in the new suite, and a continuity project in the existing one. The construction is the easier half. The harder half is the seam between the two spaces, because at some point a wall between an active clinic and a construction zone has to come down, and patients are on one side of it. Handled without a plan, that seam becomes weeks of noise, dust, and blocked corridors in the exact rooms where care is happening. Handled with the right sequence, it becomes a long quiet phase the practice barely notices, then one short, intense, scheduled connection. The difference is not effort or luck. It is the order of operations.  

The Sequence, From a Real Project

Here is how this played out on a project our team knows well: a practice of about 1,500 square feet expanding into the adjacent suite of about 1,000 square feet, while staying open throughout. Phase one built out the new suite as its own contained project, sealed off from the operating practice next door. Because the space was worked as a separate unit, the practice next door ran normally: no construction traffic through its waiting room, no dust in its exam rooms, no changes to its patient flow. That phase ended with the new suite carrying its own certificate of occupancy, meaning the space was inspected and legal to occupy on its own. Phase two turned to the connection, operating under a temporary certificate of occupancy while the two suites were joined. The heavy, disruptive part of that work, opening the wall between the spaces and tying the two suites together, was compressed into a four-day holiday weekend when the practice was closed anyway. The clinic locked its doors on a normal schedule and reopened onto a bigger practice.
“We can section ourselves off and work normal hours, aside from loud activities or activities that generate some sort of smell. Most of the time, those have to happen after hours anyway. The phasing aspect allows us to grab areas free and clear, get through them fairly quickly, and move on to the next one.” Wilson & Company, Scheduling Strategies to Keep Projects on Track
Notice what the sequence bought. The disruptive work did not shrink; it was moved to the one window where it could not disrupt anything. And the occupancy paperwork was staged so the practice was never operating in an unapproved space at any point. The same logic scales. A bigger expansion means a longer phase one, but phase one is the quiet part; the connection window stays short because it was designed to be short. What does not scale is improvisation: a connection attempted without a completed, approved suite on the other side of the wall turns a weekend into a month, with patients present for all of it.  

The Paperwork Is the Plan

The certificate of occupancy staging deserves emphasis, because it is the part practice owners do not see coming. A clinic cannot legally see patients in space that has not passed its occupancy approvals, and an expansion by definition changes what space is approved for what. Sequencing those approvals, full certificate for the new suite first, temporary certificate covering the connection work, final approval on the joined space, is what lets each phase hand off to the next without a gap in legal operation. That staging is negotiated with the building department during permitting, not improvised at the end. It is a preconstruction conversation, and it is a good test of a contractor: ask how they would stage occupancy for your expansion, and listen for a specific answer about your jurisdiction rather than a general reassurance.  

What To Settle Before Design Starts

Three things determine whether your expansion can follow this playbook. First, the adjacency itself: the suite next door has to be available, and the lease or purchase terms settled, before design money is spent. Second, the closure windows: know your practice’s natural dark days, holiday weekends, and slow seasons, because the connection work will be built around them. Third, communication: the same phase-by-phase expectation-setting that carries an occupied renovation applies here, so the front desk can tell patients exactly what changes and when. An expansion done this way is one of the most patient-friendly projects in medical construction, because nearly all of it happens on the far side of a sealed wall. If your practice is outgrowing its walls, the sequencing conversation is where to start, and it should happen before the lease on the adjacent suite is signed, not after.  

Frequently Asked Questions

Can a medical practice stay open while expanding into adjacent space?

Yes. The new space is built out as its own sealed project while the practice operates normally, then the two suites are connected during a short planned closure window, often a holiday weekend. Done in that order, patients experience almost none of the construction.

What is a temporary certificate of occupancy in an expansion?

A jurisdiction-issued approval that lets a space be legally occupied while defined remaining work is completed. In a phased expansion it bridges the connection phase, so the practice keeps operating lawfully while the two suites are joined and final approvals are finished.

How long does a medical office expansion take?

It depends on the build-out scope, but the patient-facing disruption can be compressed to days rather than months when the new suite is completed and approved before the connection is made. The full calendar runs like any build-out: design, permitting, construction, then the connection window. Continue Reading

Contact Us

1725 Kennedy Point
Ste 1001.
Oviedo, FL 32765

Phone: 407-365-0906
Fax: 407-365-0806

reach us

State License Numbers:
Florida Unlimited Certified General Contractor License CGC 1530088; Alabama State BC Building Construction 48986; Arizona – Unlimited 299503; Georgia GCCO002986; Louisiana State Contractor’s License 59276; Mississippi—Unlimited 21209-MC; Nevada – Unlimited 0080869; North Carolina State Contractor License Unlimited Building 73553; South Carolina State Contractor’s License Group 5 Unlimited G118130; Tennessee – Unlimited 67235; Texas—NASCLA; Virginia—Class A 2705169048